
ICRC · LEBANON · 2024–
Offline-first care and field infrastructure
Full clinical data captured offline, with solar power and connectivity reaching remote sites.
+40%patient documentation
Modular, reusable digital health systems, built in days, not months. Owned by you, ready to run offline, and open for others to build on.









In months, money and lost knowledge. And the systems still don’t connect.
See how we fix it ↓Every new program means a new build. Months pass before clinicians can use anything.
Every project rebuilds patient identification, lab, stock and reporting.
Clinic data rarely reaches national systems in a form anyone can use.
National strategies set a vision at scale, but rarely a practical first step.
Many sites lose power or connectivity every week.
When a consultant leaves, their knowledge goes with them, and every project relearns the same lessons.
Everything we deliver follows three principles. Each one fixes a specific problem.

A shared library of medical programs, forms and services. We standardize each one once, then assemble what each new program needs.
AI does the heavy lifting and our specialists check every output. You get systems in days, not months.
Digital public goods, offline-first and connected to national systems, then handed over to your team.
Standardized once, then set up for each new program. You start with what we've already built.

Everyday consultations and follow-up

Acute care and supporting units

Longitudinal cohorts and reporting

From pregnancy through childhood

Physical and functional recovery

Digital response within days

New use cases in climate-sensitive care: disease forecasting in DHIS2 dashboards, plus model definition and training workshops.
LIME EMR runs on OpenMRS 3 and is built from MSF protocols. It reports straight into DHIS2, and each new country reuses the same core.
“Madiro Labs builds a bridge between the complex world of open source technologies and the concrete reality of frontline MSF health workers in the field.”
Ludovic Rossel · LIME EMR Project Lead, MSF

Full clinical data captured offline, with solar power and connectivity reaching remote sites.

Lab orders and results flow automatically into DHIS2, on government-owned infrastructure.
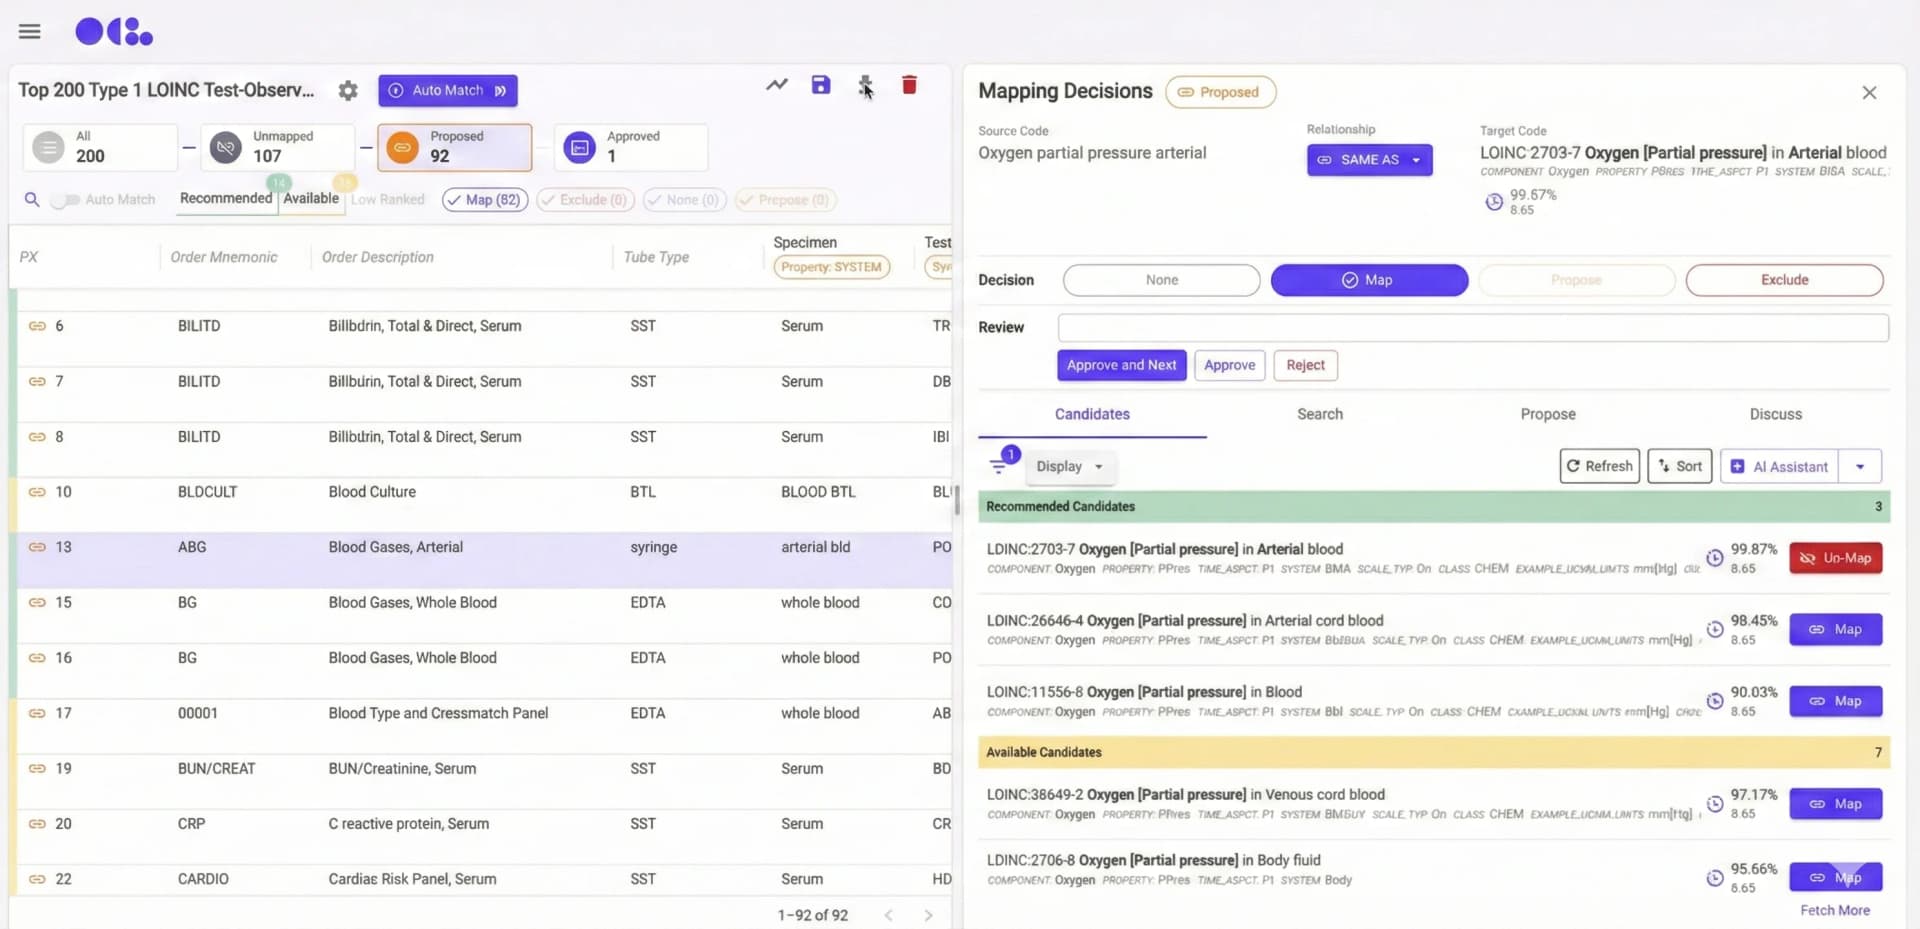
AI-first terminology mapping across 55K+ concepts. Experts validate instead of mapping by hand.
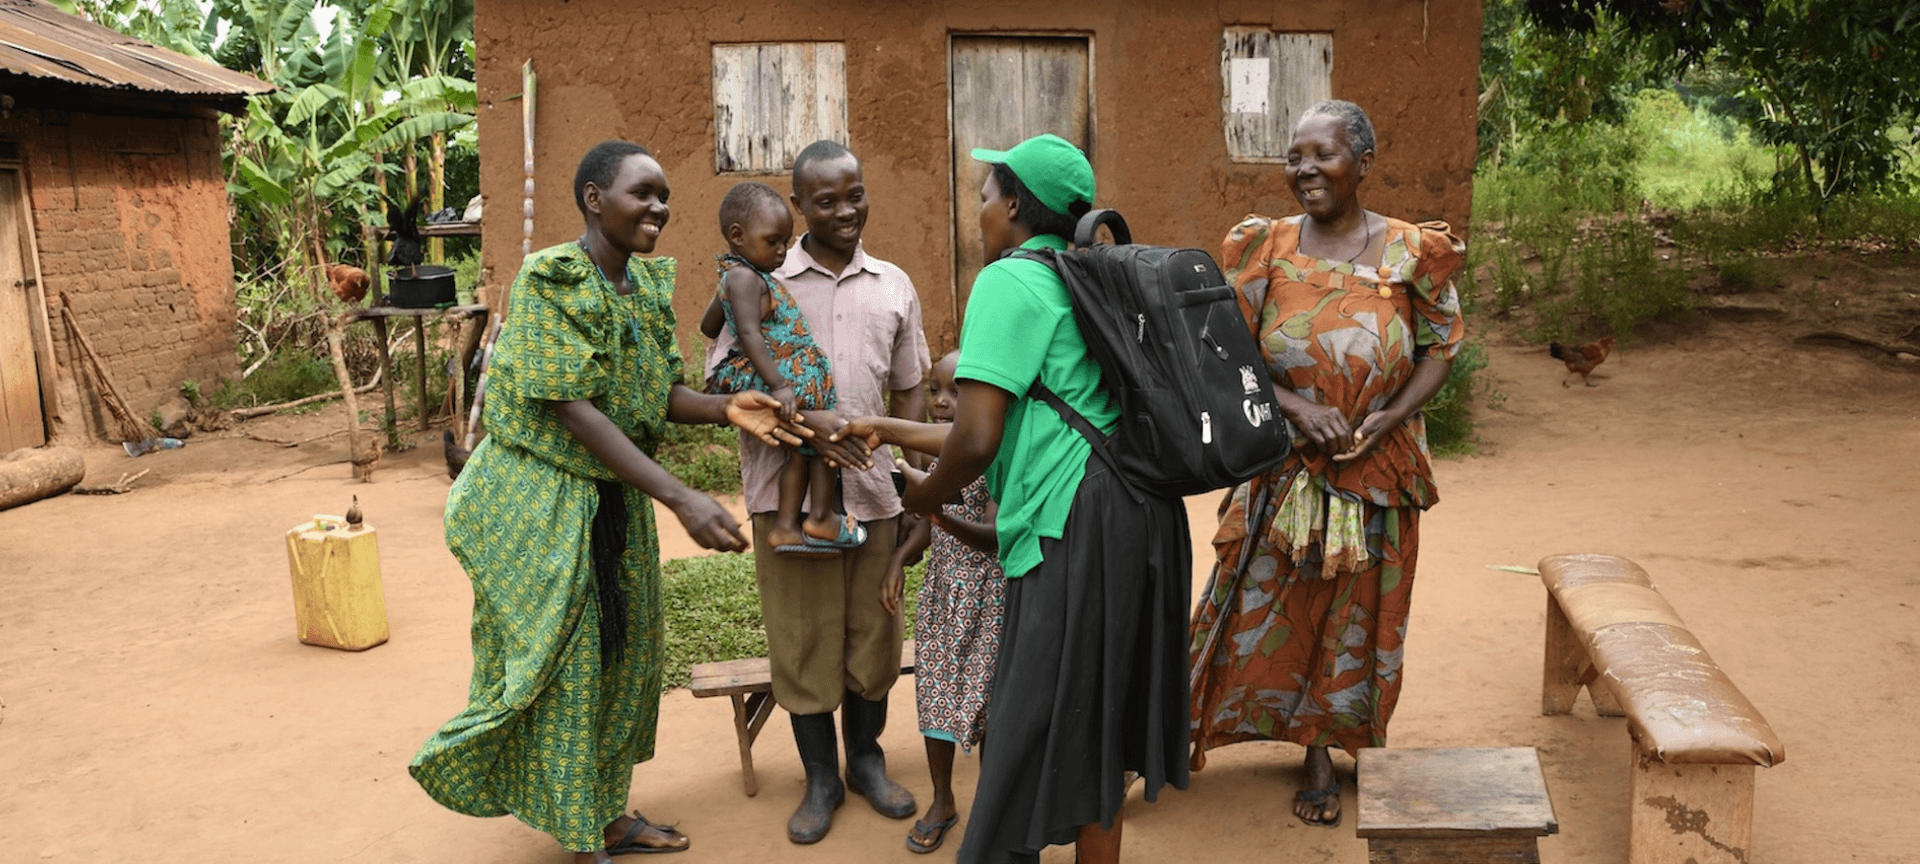
Activity, GPS and sales data combined to map how community health entrepreneurs perform.
“Madiro is positioned to be a catalyst, fostering efficiency, reducing costs, and enabling harmonious integration with national health systems.”

“OCL has become more valuable to health and humanitarian teams, with AI-assisted mapping that reflects the realities of resource-constrained systems.”

New programs need forms live across many sites, on grant timelines, with clinicians who can’t wait months.
Standardized programs (HIV, TB, maternal care, mental health and more), assembled in days and working offline.
Rapid deployments, rotating staff, unstable power and connectivity, and knowledge that leaves with each mission.
Field-proven practices, offline-first setups, and a handover designed for staff rotation.
A national vision, fragmented facility systems, and donor pilots that never connect to the national picture.
One national dictionary, facility-to-DHIS2 exchange, and code and data owned by the country.
Paying for the same build in every grant, with little evidence of adoption or of what happens after the project ends.
Fixed-price reusable packages, everything published as digital public goods, and evidence on adoption.
Strong cores, thin implementation capacity, and clinical content that every implementer rebuilds locally.
Upstream contributions to OpenMRS 3, OCL and OpenFn, plus shared clinical content libraries.
Strong local presence and client trust, with gaps in clinical informatics, terminology or FHIR.
Embedded specialists and co-bidding on tenders. Complementarity, not competition.
Informatics, clinical, OpenMRS, FHIR and data specialists, matched to your context. Non-profit in Canada, US, Switzerland and Rwanda, and a social enterprise in Canada. Launched in 2024.
Join our roster ↗Bidding on a tender, or building on the same public goods?
Partner with us →AI does the heavy lifting and our specialists check every output. That's why we're faster, and why care teams get usable patient data sooner.
Each build learns from the last one, so every new build costs less. Partners can use it too, and get the same savings on their own builds.
Onboard your team →“We see AI as an opportunity for capacity building and sovereignty, not a threat.”
Digital public goods, deployed offline-first on the infrastructure you choose, then handed to your team. Your data stays in your country, everything we build is shared back, and your total cost of ownership goes down.
A tablet, laptop or small box. Works offline where there’s no power or network.
Enterprise-grade on-premises setup, per facility or district.
Hosted in national data centres to meet data-residency rules.
Managed hosting abroad, for when scale matters most.
Open models run next to your system, with or without internet. Patient data never leaves the site, and there are no per-call AI fees.
You own the code and the data. Our code, forms and configurations are public on GitHub for anyone to reuse.
Add facilities and users without your bill growing with them.
FHIR, OpenHIE, ICD and LOINC, so your data stays portable and your system outlives any vendor, including us.
Forms, concept mappings and data pipelines go back to the community, so the next program starts ahead.
 OPEN-SOURCE EMR
 CLINICAL TERMINOLOGY
 INTEROPERABILITY





Each step builds on the one before. Buy a single piece or the whole path, with advisory at every step.
Patient records, lab, supplies, billing and reports, all from one standardized library.
The same library, mapped to international health data standards.
Clinic systems linked to national registries and reporting, owned by the country.
Offline-first, in the cloud or on-premises. Add the next site without a new build.
* Prices are indicative starting points, exclusive of taxes, and subject to change without notice. They are lower because of human-validated AI and because we reuse what’s already built. Your price is confirmed in a written scope after the discovery call. Market figures are indicative 2026 ranges, not quotes.
Describe your program, country and the systems you already use. We reply within 24 hours, or book a call directly.
 Global Digital Health Forum · Bangkok, Thailand · Dec 2 – 4

Yes. We connect the EMRs, registries and reporting platforms you already use, and standardize terminology across them following OpenHIE patterns. We only replace what isn’t working.